Prostate artery embolisation (PAE) in Sydney

Been told you need prostate surgery? PAE is a non-surgical option you can ask about. It is done through a small puncture at the wrist or groin, usually without a general anaesthetic, and you can usually go home the same day. Prostate artery embolisation (PAE) is a minimally invasive treatment for men with urinary symptoms caused by an enlarged prostate (benign prostatic hyperplasia, or BPH). It reduces the blood supply to the prostate so that it gradually shrinks, which can ease urinary symptoms. Dr Ryan McConnell, Interventional Radiologist, performs PAE at Northern Beaches Hospital and the Mater Hospital, North Sydney. A GP referral is needed. You don't need to see a urologist first.
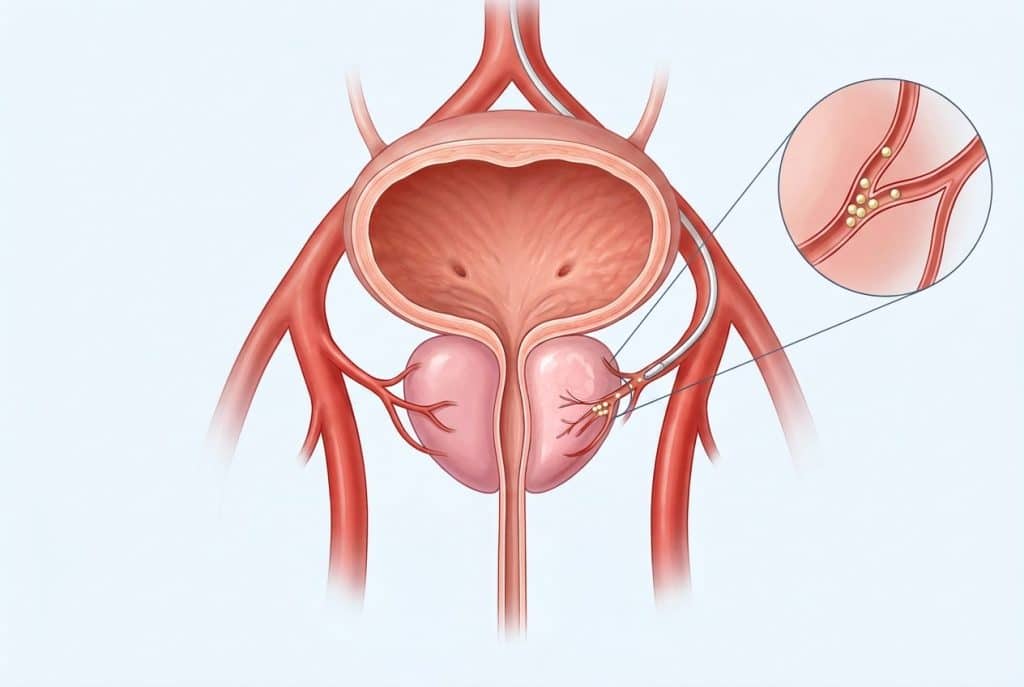
Illustration of prostate artery embolisation, showing a thin catheter in the pelvic arteries delivering tiny particles into an artery that supplies the prostate

PAE at a glance


No surgical incision

Performed through a small puncture in an artery at the wrist or groin.

Usually no general anaesthetic

Local anaesthetic, with sedation if needed.

Usually same-day

You can usually go home the same day.

Gradual improvement

Symptoms usually improve over weeks to months, not straight away.
PAE is not right for every man with an enlarged prostate. A careful assessment comes first.

What is prostate artery embolisation?


An interventional radiologist performs PAE using X-ray guidance. First, they pass a thin tube (catheter) through a small puncture in an artery at your wrist or groin. They then guide it into the arteries that supply the prostate. Next, they release tiny particles into these arteries to reduce the prostate’s blood supply. Over the following weeks and months, the prostate gradually reduces in size. As a result, it can ease pressure on the urethra (the tube that carries urine) and improve urinary symptoms.
Illustration of catheter access for prostate artery embolisation, through an artery at the groin or the wrist, to the arteries supplying the prostate

Who might prostate artery embolisation help?


PAE may be considered for men whose urinary symptoms are caused by an enlarged prostate, such as:
  • A weak or slow stream
  • Difficulty starting to urinate
  • Straining to urinate
  • Needing to urinate often
  • Sudden urges to urinate
  • Waking at night to urinate (nocturia)
  • Feeling that your bladder has not fully emptied
  • Being unable to urinate (urinary retention) because of prostate enlargement

PAE may be suitable if you:

  • have moderate to severe urinary symptoms caused by BPH
  • have an enlarged prostate, including a very large prostate
  • still have bothersome symptoms despite medication, or would prefer not to rely on tablets long term
  • have been offered TURP, HoLEP, Urolift, Rezum or Aquablation and want to understand all your options
  • would prefer a minimally invasive option, usually without a general anaesthetic

When PAE may not be suitable

PAE may not be appropriate if your symptoms have another cause. It may also not be appropriate if possible prostate cancer needs investigation or treatment first. In addition, having an enlarged prostate does not on its own mean PAE is right for you.

How suitability is assessed

Dr McConnell reviews your symptoms, prostate size and anatomy, PSA level and previous tests. Further tests may be recommended.

What happens during prostate artery embolisation?


01

Local anaesthetic and access

After local anaesthetic, Dr McConnell places a small tube in the artery at your wrist (radial artery) or groin (femoral artery).
02

Mapping the arteries

Dr McConnell uses X-ray imaging (fluoroscopy) to map the small arteries that supply the prostate.
03

Embolisation

Dr McConnell then delivers tiny particles into the prostate arteries to reduce blood flow to the targeted tissue.
04

Finishing up

Finally, Dr McConnell removes the catheter and closes the puncture site with pressure or a closure device. Afterwards, you stay for monitoring and can usually go home the same day.

How long does PAE take?

Usually about 1–2 hours, depending on your artery anatomy.

Recovery and results after PAE


01

The day of the procedure

You stay for monitoring until you are comfortable and stable. After that, you can usually go home.
02

The first few days

You may have temporary pelvic discomfort, need to urinate more often or urgently, or feel mild burning when urinating.
03

The first week

Many men return to light everyday activities within a few days, building up to more strenuous activity gradually.
04

Weeks to months

The prostate shrinks gradually. Urinary symptoms may start to improve within a few weeks, often continuing to improve over several months. How much and how quickly varies from person to person.

How long do results last?

For many men, improvement lasts several years. However, symptoms can return over time, and you may then need further assessment or treatment.

What if PAE does not help enough?

Not every man improves enough after PAE. In that case, you can still consider other medical or surgical treatments, depending on your symptoms, prostate anatomy and circumstances.

Benefits and risks of prostate artery embolisation


For suitable men, PAE can improve urinary symptoms without surgically removing prostate tissue. Like any procedure, it also carries risks.

Possible benefits

  • No surgical incision, and usually no general anaesthetic
  • Improvement in urinary symptoms and quality of life, shown in clinical studies, which develops gradually
  • A lower risk of ejaculation problems than procedures such as TURP

Common short-term effects

  • Pelvic discomfort or pressure
  • Mild pain or burning when urinating
  • Needing to urinate more often or urgently
  • A temporary worsening of urinary symptoms
  • Small amounts of blood in the urine or semen

Less common risks

  • Bleeding or bruising where the catheter was inserted (wrist or groin)
  • A urinary tract infection needing treatment
  • Injury to an artery
  • An allergic reaction to the X-ray contrast dye
  • Particles reaching tissue near the prostate (non-target embolisation)
Dr McConnell will discuss your individual risks at your consultation.

Treatment options

How does PAE compare with other enlarged prostate treatments?


The right treatment depends on how much your symptoms bother you, the size of your prostate, previous treatment and your general health. It also depends on what matters most to you, such as avoiding a general anaesthetic or preserving ejaculation.

Option

What it involves

Watchful waiting and lifestyle measures

Often suitable when symptoms are mild.

Medication

Alpha-blockers relax the muscle of the prostate and bladder neck. 5-alpha reductase inhibitors gradually reduce prostate size. They are sometimes used together.

Prostate artery embolisation (PAE)

Reduces blood flow to the prostate through a small puncture in an artery at the wrist or groin, without removing prostate tissue. Local anaesthetic, with sedation if needed. Usually same day, and a catheter is usually not needed afterwards. Lower risk of ejaculation changes than TURP. Performed by an interventional radiologist.

TURP

Removes obstructing prostate tissue through the urethra. General or spinal anaesthetic. Usually 1–2 nights in hospital, with a catheter for 1–3 days. Ejaculation is commonly affected. Performed by a urologist.

HoLEP

Uses a laser to remove obstructing prostate tissue through the urethra. General or spinal anaesthetic. Usually one night in hospital, with a catheter for 1–2 days. Ejaculation is commonly affected. Performed by a urologist.

Prostatic urethral lift (Urolift)

Small implants hold the prostate lobes apart. Local anaesthetic, sedation or general anaesthetic. Usually same day; a catheter is sometimes needed for a short time. Ejaculation is usually preserved. Performed by a urologist.

Water vapour therapy (Rezum)

Water vapour treats prostate tissue, which then shrinks over the following weeks. Local anaesthetic, with sedation if needed. Usually same day, but a catheter is often needed for several days. Ejaculation is usually preserved. Performed by a urologist.

Aquablation

A robotic water jet removes prostate tissue through the urethra. General anaesthetic. Usually 1–2 nights in hospital, with a catheter for 1–2 days. Ejaculation is less often affected than with TURP. Performed by a urologist.

Not every option suits every prostate. Some depend on prostate size and shape, and availability varies between hospitals. Dr McConnell works with GPs and urologists so that you can consider PAE alongside the other options.


Your PAE consultation


An interventional radiologist performs PAE. This is a specialist doctor trained in minimally invasive procedures guided by imaging. Dr Ryan McConnell assesses patients for PAE himself and also performs the procedure. Consultations are held at his rooms in Manly and St Leonards.
Dr Ryan McConnell

Dr Ryan McConnell

Interventional radiologist

What to bring

  • A GP or specialist referral letter
  • Previous prostate imaging reports and scans
  • Recent PSA (prostate-specific antigen) results

What happens at the consultation?

Dr McConnell reviews your symptoms, medical history and test results. You will discuss whether PAE is suitable for you, along with its risks, benefits and recovery.

Do I need to see a urologist first?

No. Your GP can refer you directly.

Frequently asked questions about prostate artery embolisation


Is PAE available in Australia?

Yes. In Australia, interventional radiologists perform PAE in hospital angiography suites.

Which hospitals offer prostate artery embolisation in Sydney?

Dr Ryan McConnell performs PAE at Northern Beaches Hospital, Frenchs Forest, and the Mater Hospital, North Sydney. The hospital is arranged after your consultation, based on your clinical needs and health insurance.

Will I need a urinary catheter after PAE?

Usually not, although one is occasionally needed. If you already have a catheter because of urinary retention, PAE may allow it to be removed, but this cannot be guaranteed.

Does PAE affect sexual function?

PAE has a low risk of affecting erections or ejaculation, because it does not remove prostate tissue through the urethra. Individual outcomes vary, and you can discuss your priorities at your consultation.

Can PAE treat a very large prostate?

Yes. Prostate size alone does not usually rule out PAE. Suitability depends on your symptoms, prostate and artery anatomy, previous treatment and overall health.

Is PAE painful?

Most men feel little discomfort during PAE. The procedure uses local anaesthetic, often with sedation. Afterwards, pelvic discomfort, frequent or urgent urination or burning can follow, and these usually settle over a few days.

How long does PAE take to work?

Improvement is gradual. Some men notice a change within a few weeks, with further improvement over the following months.

How much does prostate artery embolisation cost?

Costs depend on your health insurance, the hospital and your individual treatment plan. With a valid referral, you can claim a Medicare rebate for your consultation. If you decide to go ahead with PAE, you will receive a written estimate of fees before treatment, including what Medicare and your health fund are expected to cover. Our team can answer cost questions when you get in touch.

How soon can I be seen?

Our team will offer you the next available consultation in Manly or St Leonards when you get in touch. Having your GP referral and any recent imaging and PSA results ready helps us arrange your appointment.

Request a PAE consultation


Complete the form below and our team will contact you to discuss your enquiry and arrange a consultation where appropriate. Not ready to book yet? You can also use the form, or call (02) 9023 9970, to ask what PAE involves and what you would need from your GP. Please avoid including highly sensitive medical information in the form.

This form is not monitored for urgent medical concerns. In an emergency, call 000.

Evidence & references


This page draws on published clinical guidelines, standards of practice and peer-reviewed research on prostate artery embolisation (PAE).
  • American Urological Association (AUA) – Management of Lower Urinary Tract Symptoms Attributed to Benign Prostatic Hyperplasia: AUA Guideline (2023)
    Includes PAE as a treatment option for LUTS/BPH and recommendations regarding patient counselling and procedural expertise.
  • Cornelis FH, Bilhim T, Hacking N, et al. CIRSE Standards of Practice on Prostatic Artery Embolisation. Cardiovasc Intervent Radiol. 2020;43:176–185.
    Standards of practice addressing patient selection, technique, safety and clinical management for PAE.
  • Müllhaupt G, Hechelhammer L, Graf N, et al. Prostatic Artery Embolisation Versus Transurethral Resection of the Prostate for Benign Prostatic Obstruction: 5-year Outcomes of a Randomised, Open-label, Noninferiority Trial. Eur Urol Focus. 2024;10:788–795.
    Five-year randomised comparative outcomes for PAE and TURP.
  • Bilhim T, Costa NV, Torres D, et al. Long-Term Outcome of Prostatic Artery Embolization for Patients with Benign Prostatic Hyperplasia: Single-Centre Retrospective Study in 1072 Patients Over a 10-Year Period. Cardiovasc Intervent Radiol. 2022;45:1324–1336.
    Large long-term cohort examining symptom outcomes and subsequent treatment following PAE.
Last medically reviewed: 27 September 2026 | Medical review: Dr Ryan McConnell