
Image-guided spinal fracture treatment
Vertebroplasty
Vertebroplasty is a minimally invasive, image-guided procedure used to treat selected painful vertebral compression fractures. Bone cement is injected into the fractured vertebra through a needle to help stabilise it.
Dr Ryan McConnell performs vertebroplasty in Sydney for patients with symptomatic spinal fractures, most commonly fractures related to osteoporosis.
Whether vertebroplasty is appropriate depends on the cause and age of the fracture, your symptoms, imaging findings and overall health.
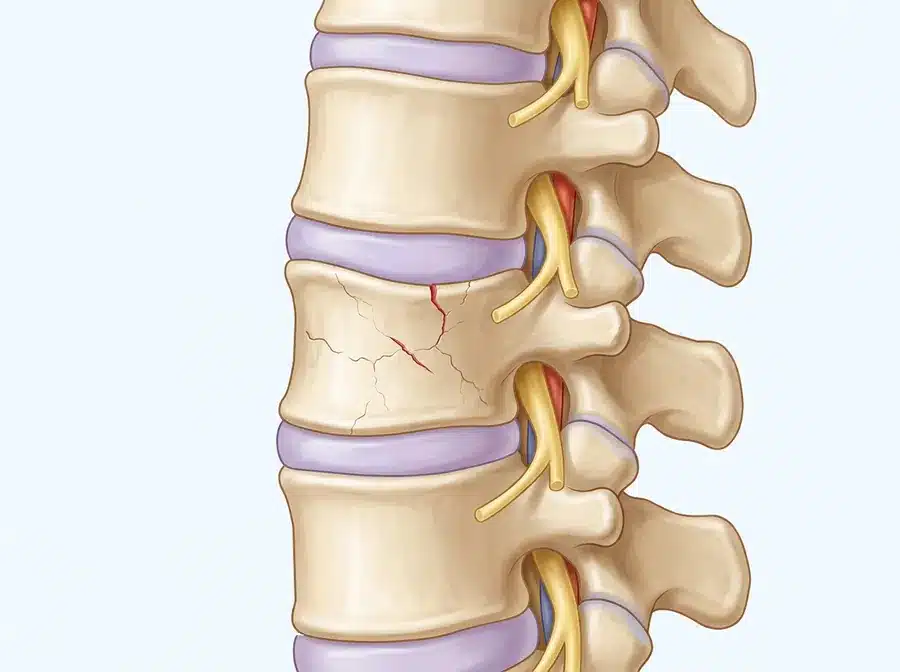
Spinal fractures
What is a vertebral compression fracture?
A vertebral compression fracture occurs when the body of a vertebra — one of the bones of the spine — partially collapses. These fractures most often affect the mid and lower back.
They are most commonly caused by osteoporosis, where weakened bone can fracture after a minor fall, lifting or sometimes no obvious injury. Less commonly, fractures can be related to other conditions that weaken the bone, including some cancers.
Symptoms vary. Some fractures cause sudden, severe back pain that is worse with standing, walking or changing position, while others cause few symptoms and are found on imaging performed for another reason.
Assessment
Who may be suitable for vertebroplasty?
Most vertebral compression fractures are managed initially with pain relief, activity modification and treatment of the underlying bone condition.
Vertebroplasty may be considered in selected patients when:
- there is a painful vertebral compression fracture confirmed on imaging
- MRI or other imaging suggests the fracture has not yet healed
- pain is significant and is not adequately controlled with conservative treatment
- the pain is consistent with the level of the fracture on examination
Who may not be suitable
Vertebroplasty may not be appropriate when a fracture has already healed, when there is infection, when bleeding risk cannot be adequately managed, or when the fracture pattern or other spinal findings make the procedure unsuitable. Your imaging and history will be reviewed before a recommendation is made.
The procedure
How is vertebroplasty performed?
Vertebroplasty is performed in a hospital procedure room using X-ray (fluoroscopy) or CT guidance.
- You lie face down while the skin over the fractured vertebra is cleaned and numbed with local anaesthetic. Sedation is commonly used.
- Using imaging guidance, a needle is passed through the skin and into the fractured vertebral body.
- Bone cement is injected slowly under continuous imaging while its spread within the vertebra is monitored.
- The cement hardens within minutes. The needle is removed and a small dressing applied.
The procedure usually takes around 30–60 minutes per level, depending on the number of vertebrae treated.
Suggested image
Side-view X-ray (fluoroscopy) image taken during vertebroplasty, showing the needle within the vertebral body and cement filling the fracture.
Vertebral augmentation
Vertebroplasty and kyphoplasty
Vertebroplasty and kyphoplasty are both forms of vertebral augmentation.
Vertebroplasty
In vertebroplasty, cement is injected directly into the fractured vertebra.
Kyphoplasty
In kyphoplasty, a small balloon is first inflated inside the vertebra to create a space before the cement is introduced.
Both aim to stabilise the fracture. The most appropriate technique depends on the fracture and individual circumstances and will be discussed with you.
After your procedure
Recovery after vertebroplasty
After the procedure you will be observed while lying flat for a period. Many patients go home the same day, although an overnight stay may be recommended depending on your circumstances.
Some soreness at the needle site is common for a few days. You will be given instructions about activity, pain relief and when to resume normal activities.
Because vertebral fractures are often related to osteoporosis, ongoing assessment and treatment of bone health with your GP or specialist is an important part of care.

Risks & considerations
What are the risks of vertebroplasty?
All procedures carry some risk. Your individual risks will be discussed before treatment.
Not every patient experiences a reduction in pain. The likely benefits and limitations will be discussed with you in the context of your fracture and symptoms.
Potential risks include:
- temporary soreness or bruising at the needle site
- cement passing outside the vertebra — usually without symptoms, but rarely it may affect nearby nerves or travel into veins
- infection or bleeding
- further fractures at other levels of the spine, which may relate to the underlying bone condition
- reaction to medications used during the procedure
FAQs
Frequently asked questions about vertebroplasty
What is vertebroplasty?
How long does vertebroplasty take?
Will I be awake?
How long does the cement last?
What is the recovery time after vertebroplasty?
What is the difference between vertebroplasty and kyphoplasty?
Do I need a referral?
Vertebroplasty
Discuss vertebroplasty with Dr Ryan McConnell
If you or your patient has a painful vertebral compression fracture, Dr McConnell can review the imaging and clinical history to help determine whether vertebroplasty may be appropriate.